



Are Credentialing Services Worth It?

Somewhere in every practice’s growth story, there’s a moment where someone asks: do we really need to pay for credentialing services, or can we just handle this ourselves? It’s a fair question. Credentialing fees show up as a clear, visible line item, while the cost of doing it in-house badly, slowly, or inconsistently tends to hide inside denied claims and delayed reimbursements that are harder to trace back to their source. Answering are credentialing services worth it honestly means looking at both sides of that ledger, not just the invoice. This isn’t a one-size-fits-all answer. But once you understand what’s actually at stake when credentialing goes wrong, the math tends to get a lot clearer. Key Takeaways What Do Healthcare Credentialing Services Actually Do? Healthcare credentialing services and provider enrollment services cover the process of verifying a provider’s qualifications and registering them with Medicare, Medicaid, and commercial payers so claims can be reimbursed. In practice, that means managing CAQH profiles, submitting PECOS applications, tracking primary source verification, handling licensing and NPI registration, and following up with payers until approval comes through. Credentialing support isn’t just filling out forms. It’s tracking dozens of moving deadlines across multiple payers simultaneously, each with its own rules, so nothing falls through the cracks while your staff focuses on patients instead of paperwork. What Happens If a Provider Is Not Credentialed? This is where the “worth it” question gets concrete. If a provider sees patients before their credentialing and enrollment are approved, claims submitted for those visits are typically denied outright, since payers have no record of that provider being authorized to bill. Billing under another, already-credentialed provider’s name to work around the gap carries serious compliance risk and can be treated as a false claim by government payers. One industry analysis lays out just how fast this adds up: a provider seeing roughly 15 patients a day at an average reimbursement of $120 per visit can generate close to $9,000 a week in billings meaning a 60-day credentialing gap can represent tens of thousands of dollars in claims that are either denied outright or subject to retroactive recoupment once the payer catches the gap. And there’s a hard deadline on fixing it: most payers only allow a limited window, often cited around 90 to 180 days from the date of service, to submit a corrected claim. Miss that window, and the revenue is simply gone. How Hard Is Insurance Credentialing, Really? Harder than it looks from the outside. It’s not one application it’s a parallel set of applications across Medicare, Medicaid, and every commercial payer a practice works with, each with different documentation standards, review timelines, and follow-up expectations. A single missing signature, an expired license, or a mismatched NPI can quietly stall an entire application for weeks. Add in the fact that most payers pull directly from a provider’s CAQH profile, which itself requires re-attestation every 120 days, and it becomes clear why practices without dedicated staff often fall behind. This is precisely the kind of ongoing tracking that dedicated credentialing solutions are built to manage, so nothing slips because someone was busy with a full patient schedule that week. What Are the Two Types of Credentialing? The two primary models are direct credentialing and delegated credentialing. Most independent practices and small groups operate under direct credentialing, which is exactly where dedicated credentialing support has the most impact, since every payer relationship has to be managed separately. The Real Cost Comparison: In-House vs. Outsourced Factor Handling It In-House Using Credentialing Services Staff time Falls on office managers or billing staff already stretched thin Managed by a dedicated team tracking every application Risk of missed deadlines Higher, especially with multiple providers or payers Lower, with structured tracking and follow-up Cost visibility Hidden in denied claims and staff hours Clear, predictable service fee CAQH maintenance Often falls behind during busy periods Maintained on a consistent schedule Recovery from a credentialing gap Slower, since gaps are often caught late Faster, with proactive monitoring Signs Your Practice Could Benefit from Credentialing Support If two or more of these sound familiar, that’s usually a sign the in-house approach is costing more than it appears to on paper. Myths vs. Facts Myth: “Credentialing services are only worth it for large hospital systems.” Fact: Smaller practices often feel the cost of credentialing gaps more acutely, since a single denied provider’s claims represent a larger share of total revenue. Myth: “If we just wait it out, the claims will eventually get paid.” Fact: Most payers only allow a limited window to resubmit corrected claims. Once that window closes, unpaid claims from a credentialing gap typically must be written off entirely. Myth: “Our biller can handle credentialing on the side.” Fact: Credentialing involves separate deadlines, documentation, and payer relationships from day-to-day billing, and treating it as a side task is a common reason applications stall. Do this, not that: Do treat credentialing as its own dedicated workflow with clear ownership. Don’t assume it will get done correctly just because someone on staff has bandwidth this month. A Familiar Scenario Consider a practice that hired a new provider and, eager to get them seeing patients, started scheduling appointments before enrollment with two major commercial payers was finalized. For weeks, the practice assumed billing was proceeding normally. It wasn’t until a batch of claims came back denied with a code nobody immediately recognized that the front office realized the gap. By the time it was resolved, several weeks of claims had aged close to the resubmission deadline, and staff spent hours untangling which visits could still be corrected. This is a pattern that shows up often in practices without a structured credentialing and enrollment support process not because anyone was careless, but because credentialing rarely gets the dedicated attention it needs when it’s squeezed between everything else on a practice manager’s plate. Bringing It Together Warren Buffett once put it simply: “Price is what you pay. Value is what you get.” That’s really
Can I Do My Own Credentialing?

Yes, a healthcare provider can handle their own credentialing. There is generally no requirement that a physician, therapist, chiropractor, supplier or other eligible provider must hire an outside credentialing company to complete enrollment applications. But being allowed to do it yourself does not necessarily make it the safest or most practical choice. The forms are only one part of the work. Successful credentialing may also require selecting the correct enrollment type, matching information across multiple systems, submitting supporting documents, responding to payer requests, tracking application status and confirming the provider’s effective date before claims are submitted. A small error may not result in an immediate denial. Instead, the application may remain pending, be returned for correction or reach approval with information that does not match the practice’s billing setup. That is why DIY provider credentialing often becomes more difficult than expected. Key Takeaways What Is Provider Credentialing? Provider credentialing is the process used to review and verify a healthcare professional’s qualifications. Depending on the organization, this may include verification of: The purpose is to determine whether the provider meets the organization’s participation or privileging requirements. However, the term “credentialing” is often used broadly to describe several different administrative processes. Credentialing, Enrollment and Contracting Are Not the Same Understanding the difference is essential before attempting the process yourself. Credentialing Credentialing verifies the provider’s professional qualifications and background. Payer enrollment Enrollment adds the provider or organization to a payer’s administrative and billing systems. For Medicare, providers and suppliers may need to complete enrollment through PECOS or the appropriate paper application. CMS explains that PECOS allows providers to enroll, upload supporting documents, sign applications electronically and manage existing enrollment information. CMS also notes that PECOS applications generally process faster than paper submissions. Contracting Contracting establishes the terms under which the provider participates in a commercial insurance network. The provider may need to review and sign a participation agreement before becoming in-network. Privileging Hospital privileging determines which procedures or services a provider is authorized to perform at a specific facility. A provider can complete one stage without completing all the others. For example, a payer may verify a provider’s credentials but still require contracting, system loading or group reassignment before claims can be paid correctly. What Does the Provider Credentialing Process Include? The exact process varies by payer, provider type and state, but it commonly includes the following stages. 1. Preparing the provider’s information Before applications begin, the provider should assemble a complete credentialing file. Commonly requested information includes: Missing one required item can prevent an application from being treated as complete. 2. Confirming the practice structure The application must reflect how the provider will actually practice and bill. Important questions include: A provider may enter individually correct information that is still wrong for the intended billing arrangement. 3. Setting up and maintaining CAQH information Many commercial payers use a centralized provider-data profile to obtain credentialing information. The profile must remain complete and consistent with the payer application. Common problems include: Completing the profile once is not enough. It must be reviewed and maintained as provider information changes. 4. Choosing appropriate payers Not every payer is equally relevant to every practice. Before submitting applications, providers should consider: Submitting an application does not guarantee network participation. A payer may have a closed panel or limited need for a particular specialty. 5. Completing payer applications Medicare, Medicaid programs, commercial insurance companies, IPAs and HMOs may each use different application systems. The information must be entered consistently across all applications. Differences involving the provider’s legal name, NPI, tax ID, address, taxonomy or group relationship can create delays later in the process. 6. Supplying supporting documents Payers may request additional documents after reviewing an application. A request may involve: These requests often have deadlines. Missing the response window may cause the payer to close or return the application. 7. Primary-source verification The credentialing organization may verify information directly with licensing boards, educational institutions, certification bodies and other authoritative sources. A provider cannot speed up every part of this process. However, incomplete or inconsistent information can cause the reviewer to stop and request clarification. 8. Committee review and approval Some applications proceed through an internal credentialing committee or approval process. Even when the provider meets the qualifications, the application may remain pending while the payer completes its internal review. 9. Contracting and system loading Commercial payer approval may be followed by contract execution and administrative loading. The provider should confirm: A congratulatory email or signed contract should not automatically be treated as proof that every billing system is ready. 10. Ongoing maintenance and revalidation Healthcare credentialing continues after initial approval. Providers may need to update: Medicare and Medicaid enrollments may also require revalidation. Commercial payer records and provider directories must be maintained as information changes. Is Provider Credentialing Hard? The individual forms are not always difficult. The difficulty comes from managing several connected systems without allowing information to conflict. A provider may need to work with: Each system may ask similar questions using different language. For example, a provider’s service location, correspondence address, billing address and pay-to address may be different. Entering the same address everywhere for convenience can create problems if it does not reflect the actual arrangement. The process also requires repeated follow-up. An application can remain pending even when the provider believes everything has been submitted. Why DIY Provider Credentialing Often Goes Wrong The wrong application is selected Individual practitioners, group practices, facilities and suppliers may require different applications. Submitting a technically complete but incorrect application can delay the process significantly. The NPI and tax structure do not match A Type 1 NPI identifies an individual provider. A Type 2 NPI identifies an organization. Using the wrong NPI or tax ID combination can affect enrollment, reassignment and claims payment. Information is inconsistent across systems A payer may compare information from several sources. Differences in names, addresses, dates or specialties can create questions even when the differences seem minor. The practice applies before it is ready
Best Practices for Provider Credentialing and Enrollment

A new provider signs their offer letter, clears their background check, and shows up ready to see patients on day one , except they can’t bill for a single visit yet. Somewhere between the signature and the first paycheck, a stack of applications, verifications, and payer reviews has to move through a system that doesn’t care how excited everyone is to get started. This is the reality of provider credentialing and enrollment, and it’s one of the most underestimated risks to a healthcare practice’s revenue cycle. Getting this right isn’t just paperwork hygiene. It’s the difference between a provider seeing patients and generating revenue from week one, or a practice absorbing months of delayed reimbursement while a new hire sits on the sidelines of the billing system. Key Takeaways What Is Provider Credentialing, Exactly? Credentialing is the process of verifying a provider’s qualifications: education, training, licensure, work history, and any disciplinary history. Enrollment is the separate step of registering that provider with specific payers , Medicare, Medicaid, and commercial insurance plans , so claims can actually be paid. Practices often use “credentialing” as shorthand for both, but understanding the split matters, because a provider can be fully credentialed and still unable to bill a payer they haven’t enrolled with yet. This distinction is exactly why a structured approach to provider enrollment matters as much as the credentialing itself. Skipping ahead on one without finishing the other is a common source of denied claims. Why Timelines Matter More Than Most Practices Expect Delays here aren’t abstract. According to MGMA’s analysis of the credentialing process, it can take 90 to 180 days between submission of a provider’s application and final credential verification and approval. For a practice bringing on a new physician or nurse practitioner, that’s potentially half a year of a fully staffed, fully trained provider unable to generate reimbursable revenue through most payers. You’ve probably felt this if you’ve ever managed onboarding: the provider is present, the schedule is filling up, and yet claims are piling up in a “pending credentialing” bucket that nobody wants to look at too closely. The 5 Best Practices That Actually Move the Needle Most credentialing advice repeats the same generic checklist. Here’s the version that focuses on what actually prevents delays: A Simple Framework for Reducing Delays Practice When It Helps Most A Simple Cue Common Mistake Early document collection New provider onboarding Request documents the day the offer is signed Waiting until the start date to begin paperwork CAQH profile accuracy Before any payer submission Re-attest every 120 days without exception Letting the profile lapse or go stale Medicare-first sequencing Multi-payer enrollment Submit PECOS application before commercial plans Submitting commercial and Medicare applications out of sync Centralized tracking Practices onboarding multiple providers One shared tracker for every application’s status Relying on individual staff memory or scattered emails Scheduled payer follow-up Long-pending applications Check in weekly, not only when a denial appears Waiting passively for payers to respond What Should You Prepare Before You Even Start? Here’s the direct answer: a complete, verified document package speeds up nearly every stage of both credentialing and enrollment. At minimum, that means: Gaps or inconsistencies in any of these are among the most common reasons applications get returned for correction, which resets the clock on an already long process. Myths vs. Facts About Credentialing and Enrollment Myth: “Credentialing and enrollment are the same process.” Fact: Credentialing verifies a provider’s qualifications; enrollment registers them with specific payers so claims can be reimbursed. A provider can be credentialed and still not enrolled with a given plan. Myth: “Once CAQH is done, the process is basically finished.” Fact: CAQH completion is one input into payer review, not an approval itself. Commercial payers, Medicare, and Medicaid each still conduct their own separate review and approval process. Myth: “Outsourcing credentialing is only worth it for large practices.” Fact: Smaller practices often lose more, proportionally, to delayed reimbursement and denied claims from in-house credentialing gaps than they would spend on a dedicated credentialing solution. Do this, not that: Do treat credentialing as a parallel track that starts on day one of employment. Don’t treat it as a formality to handle after the provider already has a full patient schedule. A Familiar Scenario Picture a growing multi-specialty practice bringing on two new providers in the same month. The front office is focused on scheduling, onboarding, and EHR access , understandably so. Credentialing gets handed to whoever has time between other tasks, and CAQH profiles sit half-finished for weeks. By the time applications go out, Medicare and three commercial payers are all moving on different timelines, with no single person tracking which payer is waiting on which document. Three months later, both providers are seeing full patient loads, but a growing stack of claims sits unpaid, waiting on enrollment that should have started the day their offer letters were signed. This is less a rare mishap than a pattern that shows up in practices without a dedicated credentialing solutions process , which is exactly the gap that a structured credentialing and enrollment partner is built to close. Bringing It Together As management theorist W. Edwards Deming put it, “If you can’t describe what you are doing as a process, you don’t know what you’re doing.” Credentialing and enrollment reward exactly that mindset , a defined process, tracked consistently, beats scrambling reactively every time. The practices that treat this as a structured workflow, starting the day an offer letter is signed, consistently see shorter timelines and fewer denied claims than those that treat it as an afterthought. If your practice is bringing on new providers, or finding that credentialing keeps eating into staff time better spent elsewhere, it may be worth having a dedicated team handle it. Easy Billing Services’ credentialing solutions cover provider enrollment, CAQH setup and maintenance, licensing, NPI registration, and hospital privilege applications for all provider types in all states , built specifically to keep this process from becoming the bottleneck it
Outsource Credentialing Services: What It Means and Why So Many Practices Are Making the Switch
A hospital administrator once described her credentialing workload like juggling with one hand tied behind her back , fifteen providers, six payer panels each, and a spreadsheet that only she fully understood. When she went on medical leave for two weeks, three re-credentialing deadlines slipped through unnoticed. The fix wasn’t a better spreadsheet. It was recognizing that credentialing had outgrown what any single in-house employee could reliably manage alone. That’s the exact realization driving more practices and hospitals to outsource credentialing services every year. Key Takeaways What Does It Mean to Outsource Credentialing Services? Outsourcing credentialing means partnering with a specialized company that handles the entire process on your behalf , primary source verification, payer applications, CAQH profile management, follow-up calls, and ongoing re-credentialing. Rather than managing every payer application internally, your practice hands that workload to a team that does this daily, across hundreds of providers and payer relationships. This is different from simply buying credentialing software. A software platform gives you tracking tools, but someone still has to do the actual work of submitting applications and following up with payers. Full-service medical credentialing solutions include that labor, not just the dashboard. Why Practices and Hospitals Are Outsourcing Credentialing The case for outsourcing comes down to speed, accuracy, and freeing up internal staff for higher-value work: Who Actually Benefits From Outsourcing Credentialing? Outsourcing isn’t just for large systems , it scales down just as well as it scales up: What’s Included in Full-Service Credentialing and Enrollment Services Service Component What It Covers Initial credentialing Primary source verification, license checks, background and malpractice history review Provider enrollment Payer-specific applications for Medicare, Medicaid, and commercial insurers CAQH management Profile setup, ongoing attestation, and data accuracy checks Contracting support Negotiating and managing payer contracts as part of credentialing and contracting services Compliance monitoring Exclusion list checks, license expiration tracking, and re-credentialing scheduling Status reporting Regular updates so your team always knows where each application stands The Fastest Way to Get Professional Credentialing Services Set Up Do This, Not That: Getting Outsourcing Right A Familiar Scenario: The Group Practice That Stopped Firefighting Overview: A seven-provider multi-specialty group had one office manager handling credentialing alongside a dozen other responsibilities, using little more than a shared spreadsheet to track deadlines. What happened: Insight: As Henry Ford once put it, “coming together is a beginning, staying together is progress, working together is success.” Outsourcing credentialing isn’t about giving up control , it’s about partnering with a team built specifically to keep the process moving. Finding the Right Credentialing Partner for Your Practice Among the many credentialing and enrollment services available, the right fit depends on your provider count, specialties, and payer mix. Easy Billing Services offers full credentialing solutions , including Medicare and Medicaid enrollment, CAQH management, commercial payer credentialing, contracting support, and DME-specific accreditation , built for solo practices, growing groups, and larger organizations alike. Ready to hand off the paperwork? Call Easy Billing Services at (877) 306-2906 or email info@easybillingservices.com to talk through your credentialing needs. Frequently Asked Questions What does it mean to outsource credentialing services? It means partnering with a specialized company to handle the full credentialing process , verification, payer applications, CAQH management, and ongoing compliance , instead of managing it with internal staff. What are the best credentialing services for a growing practice? The best fit depends on your provider count and payer mix, but look for a partner with strong first-time approval rates, transparent pricing, and experience with your specific specialties. Is Easy Billing Services a hospital credentialing company, or just for smaller practices? Easy Billing Services supports practices of every size, from solo providers to larger, multi-provider organizations with more complex payer and contracting needs. What’s included in provider enrollment and credentialing services? Typically primary source verification, payer-specific enrollment applications, CAQH profile management, contracting support, and ongoing compliance monitoring. How is medical billing and credentialing services different from credentialing alone? Combining both means the same partner manages provider enrollment and the billing process together, which helps prevent the revenue gaps that happen when enrollment and billing are handled separately. What’s the fastest way to get professional credentialing services for a new hire? Start the process as early as possible , ideally 90 to 120 days before a provider’s start date , and hand off documentation and CAQH access right away so verification isn’t delayed by missing paperwork. Do outsourced credentialing companies handle re-credentialing too? Yes, ongoing re-credentialing and compliance monitoring are typically included as part of full-service credentialing and enrollment services, not just the initial application.
How to Select the Best Credentialing Company for Your Practice
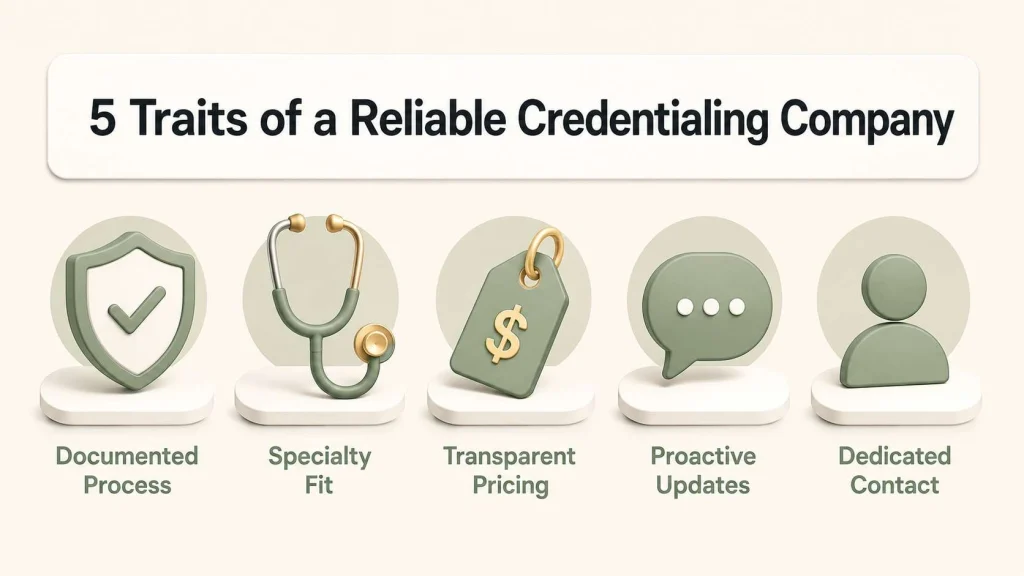
Imagine two clinics hiring their first nurse practitioner in the same month. One clinic picks a credentialing partner based on a fast phone call and a low quote. The other spends an extra week asking the right questions before signing anything. Ninety days later, one provider is seeing insured patients and generating revenue. The other is still stuck in a payer queue, and nobody can explain why. That gap didn’t come down to luck. It came down to how each clinic selected its credentialing company. Choosing a credentialing partner feels like a back-office decision, but it behaves like a revenue decision. The right company gets providers approved and billing sooner. The wrong one creates delays that are hard to trace and even harder to fix once they’ve already cost you weeks of reimbursement. Key Takeaways Why the Credentialing Company You Pick Actually Matters Credentialing determines when a provider can start billing insurance. Pick a company that’s disorganized, slow to communicate, or unfamiliar with your specialty, and every one of those problems becomes your practice’s problem , usually in the form of delayed reimbursements and frustrated new hires. It also matters more than it used to. Credentialing oversight tightened significantly in 2025, when the National Committee for Quality Assurance (NCQA) shortened its primary source verification window from 180 days to 120 days for accredited organizations, and to 90 days for certified ones, specifically to keep provider data current and get practitioners into networks faster. A credentialing partner that hasn’t adjusted its workflow to these tighter standards is already operating behind the current bar. (source) What Actually Separates a Good Credentialing Company From a Mediocre One A credentialing company’s job sounds simple: verify a provider’s qualifications and get them approved with payers. In practice, that job involves dozens of moving pieces , CAQH profile management, payer-specific application requirements, primary source verification, and relentless follow-up. The companies that do it well share a handful of traits that are easy to check for before you sign anything. In-House Team, Software Platform, or Full-Service Company: How Do They Compare? (Figures below are general guidance for planning purposes; actual fit depends on your practice size and growth pace.) Approach What You Get Best Fit For Watch Out For In-house credentialing staff Full control, direct oversight Larger groups hiring providers regularly Salary, training, and turnover costs Credentialing software only Tracking dashboards and reminders Practices that already have staff to do the work Software still requires someone to execute the process Full-service credentialing company End-to-end handling, from documents to payer approval Growing practices, multi-payer panels, DME and Medicare enrollment Confirm exactly what’s included before signing Delegated / NCQA-certified CVO Verified process aligned to national standards Organizations that need audit-ready compliance Fewer providers offer true delegated credentialing Is a Slower, Cheaper Option Ever the Right Call? Sometimes. A solo provider joining two payers with plenty of admin time might not need a full-service partner. But as soon as a practice is hiring regularly, working across several payers, or managing Medicare, Medicaid, and commercial credentialing at once, the value of a documented, accountable process starts to outweigh the appeal of the lowest quote. As Warren Buffett once put it, “it takes 20 years to build a reputation and five minutes to ruin it” , and few processes put a practice’s reputation and cash flow at risk faster than an unreliable credentialing partner. Choosing based on trust and track record, not just price, tends to hold up better over time. The Five-Question Framework for Vetting Any Credentialing Company Before signing with any credentialing partner, ask these five questions directly: A Simple Checklist for Comparing Your Top Two or Three Options Do This, Not That: Common Mistakes When Choosing a Credentialing Partner A Familiar Scenario: The Clinic That Switched Credentialing Partners Mid-Process Overview: A three-provider clinic hired a credentialing company based on the lowest quote they received, without checking accreditation status or asking for specialty references. What happened: The turnaround: Insight: The lowest quote wasn’t actually the cheapest option once six weeks of stalled revenue were factored in , the clinic paid for the switch, but paid far more for the delay that made it necessary. Making the Final Call Selecting a credentialing company comes down to matching your practice’s size, specialty, and growth pace with a partner that has a documented process, relevant experience, and communication you can count on. Price matters, but it shouldn’t be the deciding factor on its own , a slightly higher fee from a reliable, NCQA-aligned partner is almost always cheaper than months of stalled reimbursements from an unreliable one. For practices weighing this decision, Easy Billing Services offers full credentialing solutions covering Medicare and Medicaid enrollment through PECOS, commercial payer credentialing, CAQH setup and attestation, NPI registration, hospital privilege applications, and DME-specific accreditation , all handled with a dedicated team rather than a rotating inbox. Before your next hire starts the clock, it’s worth confirming exactly who will be handling their credentialing and how. Ready to talk through your options? Call Easy Billing Services at (877) 306-2906 or email info@easybillingservices.com for a straightforward conversation about your practice’s credentialing needs. Frequently Asked Questions How can Easy Billing Services help me choose the right credentialing approach? Easy Billing Services works directly with practices to handle Medicare, Medicaid, commercial payer, and DME credentialing, offering a dedicated team and clear, itemized pricing so you know exactly what’s included from the start. Does Easy Billing Services handle credentialing for specialties beyond DME? Yes. Their team supports provider enrollment, CAQH management, NPI registration, and hospital privileging across a range of specialties and provider types, not only DME. How do I select the best credentialing company for my practice? Look for NCQA accreditation or certification, direct experience with your specialty, a transparent and itemized fee structure, and a dedicated point of contact who provides regular updates. Is NCQA accreditation necessary for a credentialing company? It isn’t legally required, but it’s one of the clearest signs a company follows a documented, monitored,
How Much Does Credentialing Cost? A Clear Breakdown for Healthcare Practices

Picture a nurse practitioner who just joined a busy family practice. Her license is active. Her malpractice coverage is signed. Her schedule is already filling up. But two months later, she’s still seeing only a trickle of patients, because her insurance paperwork hasn’t cleared yet. Every day she waits, real revenue quietly walks out the door. That’s the hidden weight behind one deceptively simple question: how much does credentialing cost? It sounds like it should have a one-line answer. It doesn’t. The number depends on how many payers you’re joining, what kind of provider you’re credentialing, and whether you handle the paperwork yourself or hand it to someone who does this every day. But once you understand the moving parts, the cost stops feeling like a mystery and starts feeling like something you can actually plan for. Key Takeaways What Credentialing Actually Is (In Plain Terms) Credentialing is the process of proving a provider is who they say they are and qualified to do the job. Insurance companies, hospitals, and government programs verify a provider’s education, licenses, work history, and malpractice record before they’ll allow that provider to bill them. No credentialing, no reimbursement ,it’s really that direct. Behind that one-sentence definition sits a stack of paperwork: CAQH profile setup, license verification, background checks, malpractice history, and a separate application for every single payer a provider wants to join. Multiply that by however many insurance panels your practice works with, and you can start to see why the cost question doesn’t have a flat answer. How Much Does Credentialing Cost? For a single provider joining a single insurance payer, professional credentialing services typically charge between $200 and $500. That fee covers gathering documentation, submitting the application, and following up until the provider is approved. Add every payer a provider needs ,several commercial plans plus Medicare and Medicaid ,and most practices end up spending somewhere between $2,000 and $5,000 per provider in the first year, once setup fees, CAQH management, and follow-up work are included. That range moves depending on three things: how many payers you’re enrolling with, how complex the provider’s specialty is, and whether a practice handles the process in-house or brings in outside help. A solo behavioral health provider joining three payers pays very differently than a multi-specialty group onboarding five new physicians at once. What Pushes Credentialing Costs Higher or Lower? A few variables explain almost all of the swing between a modest bill and an expensive one: A Quick Look at Typical Costs by Approach (Figures below are general ranges for planning purposes; your actual cost will depend on your state, specialty, and payer mix.) Approach Typical Cost Range Best Fit For Where Costs Sneak Up Handling it yourself Staff time worth roughly $750–$1,500+ per provider, plus payer fees Very small practices with spare admin hours Missed deadlines and resubmissions Professional credentialing service Roughly $200–$500 per payer, or $2,000–$3,000+ per year per provider for full service Growing practices with multiple payers Setup fees and ongoing CAQH upkeep Full-time in-house specialist $50,000–$80,000+ in annual salary and benefits Larger groups hiring providers regularly Turnover, training, and slow seasons with underused staff Hospital privileging $500–$1,500+ per provider, separate from payer enrollment Providers who need hospital privileges Assuming it’s bundled into payer credentialing when it isn’t In-House vs. Outsourced Credentialing: Which One Actually Costs More? On paper, doing credentialing in-house looks like the cheaper option, because there’s no vendor invoice. In practice, a single application can take four to eight hours to complete correctly, and a provider joining five or more payers can easily consume 20-plus staff hours between paperwork, follow-up calls, and fixing small errors that trigger a rejection. Multiply that by an office manager’s hourly rate, and the “free” option often costs more than a flat-fee service ,without the benefit of someone who already knows exactly what each payer wants to see. Outsourcing shifts that cost from unpredictable staff hours into a fixed, plannable number. It also tends to shorten the waiting period, which matters more than most owners expect. As Benjamin Franklin put it, “By failing to prepare, you are preparing to fail” ,and few processes reward preparation the way credentialing does. The Four Levers That Really Control Your Credentialing Bill Instead of thinking of credentialing as one flat fee, it helps to think of it as four levers you can actually pull: A Simple Way to Budget for Credentialing Before You’re Surprised by It Do This, Not That: Mistakes That Quietly Inflate the Bill The cost of getting this wrong is bigger than most practices expect. According to the Medical Group Management Association, a 2019 Merritt Hawkins survey found that a one-day delay in provider onboarding can cost a medical group over $10,000 ,a reminder that the real expense of credentialing usually isn’t the application fee at all. It’s the revenue that never gets billed while paperwork sits in a queue. (source) A Familiar Scenario: The New Provider Who Almost Cost Two Months of Revenue Overview: A small multi-provider clinic hired a new physician assistant, expecting her to start seeing patients within two weeks of her official hire date. Nobody had started the payer applications until her first day. What happened: The turnaround: Insight: The clinic didn’t pay more for credentialing help ,it paid for the two months of lost billing that happened before it asked for help. Is Paying for Professional Credentialing Support Worth It? For a solo provider joining two or three payers, doing it yourself might genuinely make sense. But for practices onboarding providers regularly, working across multiple payer panels, or managing Medicare, Medicaid, and DME enrollment at the same time, the math tends to favor outside support ,not because it’s cheaper on the invoice, but because it protects the revenue that would otherwise sit in limbo. That’s the exact gap Easy Billing Services was built to close. Beyond DME and Medicare billing, their team handles Medicare, Medicaid, and commercial provider enrollment, CAQH setup and attestation, NPI registration, hospital privilege applications, and
The Credentialing Process for Healthcare Providers: Why It Takes So Long and How to Move It Faster
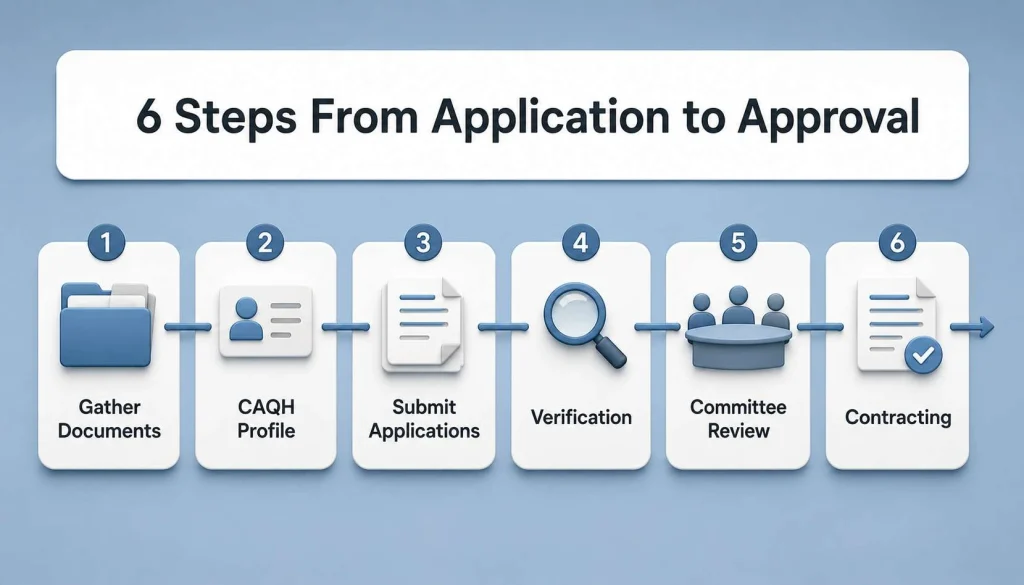
A new physician signs an offer letter, sets up an exam room, and expects to start seeing patients within a few weeks. Then the calendar quietly slips. Six weeks pass. Then ten. The provider is fully licensed, fully qualified, and still can’t bill a single insurance company. This isn’t a rare hiccup. It’s the credentialing process for healthcare providers doing exactly what it’s designed to do , verify every credential, one payer at a time , just slower than most practices plan for. Understanding how this process actually works, and where it typically stalls, is the difference between a provider who’s billing within two months and one who’s still waiting at month five. Key Takeaways What Is the Credentialing Process for Healthcare Providers? Credentialing is the process payers and healthcare organizations use to verify a provider’s education, training, licensure, work history, and malpractice record before allowing that provider to treat patients under their network or bill for services. It relies on primary source verification , confirming information directly with the issuing institution, not just accepting a copy of a diploma. Provider enrollment is the next step: once credentials are verified, the provider applies to join a specific payer’s network so claims can actually be reimbursed. Practices often use “credentialing” as shorthand for both steps combined, which is part of why the timeline feels murky from the outside. Medical Credentialing Steps, In Order The provider credentialing process generally follows the same sequence regardless of specialty or payer: This is the sequence most credentialing checklist resources circle back to, because skipping or rushing any single step is what pushes approval past the standard window. How Long Does the Credentialing Timeline Actually Take? Ask most practice managers, and they’ll say credentialing “takes about three to four months.” That’s a fair average, but it hides a wide range depending on the payer and how clean the application is. Standard commercial payer credentialing generally runs 90 to 120 days once a complete CAQH profile and application are submitted. Medicare enrollment through PECOS often moves faster, typically 60 to 90 days. Medicaid varies significantly by state. And the National Committee for Quality Assurance, which accredits many payer credentialing programs, sets a 180-calendar-day verification time limit as the outer boundary organizations must work within. (NCQA, Credentialing and Provider Network Standards) What pushes a file past that window almost always comes down to documentation, not the provider’s qualifications. A single missing signature, an unexplained employment gap, or a CAQH profile that hasn’t been attested in the last 120 days can each add weeks. What Are the Medical Credentialing Requirements? Every payer has its own application format, but the underlying medical credentialing requirements are consistent: Payers won’t begin substantive review until every required field is complete , a profile sitting at 95% complete is, functionally, not started. Document Type Purpose Who Provides It Common Mistake CAQH Profile Central data source most payers pull from Provider or credentialing staff Incomplete sections or lapsed 120-day attestation State License Confirms active, unrestricted practice authority State licensing board Expired license uploaded instead of current one Malpractice Insurance Verifies current and historical coverage Insurance carrier Missing historical coverage years Work History Explains professional background, no unexplained gaps Provider Gaps over 90 days left unexplained Board Certification Confirms specialty qualification Certifying board Expiration date not tracked Physician Credentialing vs. Provider Enrollment: What’s the Difference? Physician credentialing confirms a provider is qualified to practice. Provider enrollment is the separate process of joining a specific payer’s network so that provider’s claims get paid. A physician can be fully credentialed and still unable to bill a particular insurer until enrollment with that specific payer is complete. This distinction matters because practices sometimes assume credentialing alone means a provider is ready to see insured patients. In reality, both steps need to finish, payer by payer, before billing can begin cleanly. Insurance Credentialing Mistakes That Slow Everything Down Most delays trace back to a short list of repeat mistakes. Do this, not that: As Peter Drucker put it, “What gets measured gets managed” , and credentialing timelines are no exception. Practices that track each application’s status weekly close files faster than those that check in only when a provider asks why they still can’t bill. A Familiar Scenario: The Six-Month Wait Picture a family medicine practice bringing on a new physician in January, expecting to start billing by March. The provider’s CAQH profile looked complete at a glance, but one malpractice coverage year was missing from the documentation. The payer didn’t flag it immediately , the application simply sat in a pending queue for weeks with no visible movement. By the time the gap was caught and corrected, the practice had lost nearly two additional months of billable revenue for that provider, on top of the original 90-day estimate. This is one of the more common patterns in provider enrollment services: not a disqualifying issue, just a small documentation gap that went unnoticed until it had already cost real time. Payer Enrollment Process: What Happens After Approval Once a payer approves a provider, enrollment isn’t quite finished. The provider needs a confirmed network effective date, and any claims billed before that date typically won’t be paid, even if the approval letter has already arrived. Tracking effective dates carefully , and holding claims until the date is confirmed , prevents a second, avoidable wave of denials right after a provider clears credentialing. A Simple Credentialing Checklist Before submitting any application, confirm: Five checks. A few minutes to review. It’s a small habit that prevents the majority of preventable delays. Bringing It Together The credentialing process for healthcare providers isn’t designed to be an obstacle course , it exists to confirm, with real verification, that every provider treating patients and billing payers is who and what they claim to be. When the CAQH profile, supporting documents, and payer applications are complete and consistent from the start, most files move through in the standard 90 to 120 day window instead of drifting
DME Documentation Requirements: What Actually Keeps Your Claims From Getting Denied

A biller pulls up a denied claim on a Tuesday morning. The wheelchair was medically appropriate. The patient needed it. The supplier delivered it on time. And yet the claim bounced back with a code that has nothing to do with the equipment and everything to do with paperwork. This happens more often than most practices expect. Getting DME documentation requirements right isn’t about drowning in forms , it’s about knowing exactly which pieces of paper Medicare and other payers actually check, and making sure each one tells the same story: this patient needed this equipment, and here’s the proof. If you bill for durable medical equipment, or you’re the practice staff generating the orders that suppliers depend on, this is the part of the process that decides whether reimbursement shows up on schedule or gets stuck in appeals for months. Key Takeaways Why DME Claims Get Denied More Than You’d Think Ask any experienced biller who handles DME billing what trips up claims, and equipment eligibility rarely tops the list. Paperwork does. Federal audit data backs this up. In its fiscal year 2025 review of the Medicare fee-for-service program, the Centers for Medicare & Medicaid Services reported a national improper payment rate of 6.55%, representing $28.83 billion in improper payments , and documentation gaps remain a leading driver of that figure across claim types, including DME. (CMS, FY2025 CERT Report) What does that actually mean for a DME supplier or billing team? It means a technically valid, medically appropriate piece of equipment can still get denied because the record didn’t prove what it needed to prove, in the format the payer requires. Medicare reviewers aren’t reading your documentation the way a treating physician would. They’re checking boxes against a coverage policy , and if a box is empty, the claim fails, no matter how clinically sound the decision was. What Counts as DME Documentation? DME documentation is the set of records that together prove a piece of equipment was medically necessary, properly ordered, and actually delivered to the patient. It typically includes a signed order, clinical notes supporting the diagnosis and functional need, a letter of medical necessity when required, and a delivery confirmation signed by the patient or caregiver. No single document carries the claim on its own. Payers look at the full picture , and a gap in any one piece can undo the rest. The Core DME Documentation Checklist Think of DME billing documentation as five interlocking pieces. Miss one, and the claim’s foundation is incomplete. This is the sequence most dme documentation checklist resources circle back to, because it mirrors exactly what a Medicare Administrative Contractor reviews line by line. What Does Medicare Require for DME Documentation? Medicare’s rules are the strictest baseline most payers work from, so getting Medicare DME documentation right tends to satisfy commercial payers too. Two things matter most: timing and specificity. The order has to exist before the equipment is delivered, not backfilled afterward. And the clinical notes have to name the specific diagnosis, functional limitation, and equipment , generic phrases like “patient needs mobility assistance” without supporting detail are a common reason claims stall. Local Coverage Determinations (LCDs) add another layer. Certain HCPCS codes , CPAP devices, oxygen concentrators, power wheelchairs , carry their own specific documentation requirements, like a qualifying sleep study result or a face-to-face mobility evaluation. Skipping the LCD-specific requirement is one of the most preventable reasons proof of medical necessity gets rejected. Document Type Purpose Who Provides It Common Mistake Written Order (WOPD) Establishes what was ordered and why Treating practitioner Verbal-only order, missing date or signature Letter of Medical Necessity Explains clinical justification Practitioner or clinical staff Generic wording without diagnosis specifics Clinical/Progress Notes Supports diagnosis and functional need Treating practitioner Notes don’t mention the equipment at all Proof of Delivery Confirms patient received the item Supplier Missing patient signature or vague item description CMN / DIF Required for specific HCPCS categories Practitioner, co-signed by supplier Expired or outdated form used Documentation Errors in DME Billing to Avoid Most dme claim documentation errors repeat across practices and suppliers. A few show up constantly: Do this, not that: As Benjamin Franklin put it, “An ounce of prevention is worth a pound of cure” , and in DME billing, that ounce is a completed checklist before the claim goes out the door, not an appeal letter after it comes back. A Familiar Scenario: The Missing Signature Picture a mid-sized DME supplier delivering a hospital bed to a homebound patient. The order was correct. The clinical notes supported the diagnosis. But the delivery ticket only had the driver’s initials , not the patient’s or caregiver’s signature. Weeks later, the claim was flagged during a routine audit. Everything else in the file was solid, but that one missing signature meant the payer couldn’t confirm the equipment actually reached the patient. The claim was denied, and the supplier had to track down the patient’s family for a retroactive attestation , a slower, harder path than getting the signature right the first time. This kind of gap is common, and it’s almost always avoidable with a short intake and delivery checklist that front-line staff actually use. What Happens During a DME Documentation Audit? DME audit documentation reviews (Targeted Probe and Educate, RAC audits, or CERT sampling) follow a similar pattern: the contractor requests the full file, checks it against the applicable coverage policy element by element, and flags anything missing or inconsistent. There’s little room for clinical judgment to fill a documentation gap , if the record doesn’t show it, the reviewer treats it as if it didn’t happen. That’s why building documentation habits before an audit request lands is far less costly than reconstructing records after the fact. A Simple Pre-Submission Checklist Before a DME claim goes out, run it through this DME billing checklist: Five questions. A few minutes per claim. It’s a small habit that prevents a disproportionate share of denials. Bringing It Together DME documentation
DME Compliance in 2026: What Every Provider Needs to Know

DME compliance has always required attention. But 2026 is a different kind of demanding. Payers are leaning harder on automated review systems. Documentation expectations keep getting tighter. And the margin for error in billing , already thin , is shrinking further. For providers running DME operations, the day-to-day pressure of staying compliant while keeping cash flow steady is genuinely difficult. The challenge most teams face isn’t a lack of effort. It’s that the rules keep shifting, and keeping up requires systems that simply aren’t in place yet. This guide breaks down what’s actually happening with DME compliance this year, what risks to watch, and what practical steps make the biggest difference. Why DME Compliance Feels Different in 2026 A few years ago, a missed detail in a claim might have taken weeks to surface. Now, automated payer systems flag inconsistencies almost immediately. The U.S. Department of Health & Human Services Office of Inspector General has consistently prioritized healthcare billing oversight as a federal enforcement focus. For DME providers specifically, that means more scrutiny on documentation, coding, and authorization management , not less. What this creates operationally is a compliance environment where small gaps have bigger consequences than they used to. A missing signature on a physician order. An expired authorization that slipped through. An eligibility status that changed three days before delivery. Each of these used to be manageable. Now they can trigger denials, audits, or delayed reimbursements that ripple through your cash flow for weeks. The providers managing this well in 2026 are not necessarily larger organizations. They’re the ones who built compliance into their daily workflow rather than treating it as a last-step review. The 5 Biggest DME Compliance Risks Right Now 1. Incomplete Documentation Documentation is still the leading cause of claim denials in DME billing. And “mostly complete” does not hold up under audit review. Payers want to see medical necessity clearly supported. Physician orders properly signed and dated. Delivery confirmations on file. Authorization records organized and accessible. Every piece needs to be there , not just most of them. The fix for most providers isn’t working harder. It’s standardizing the intake process so documentation gets captured correctly from day one. Internal documentation audits , even monthly spot checks , catch gaps before they reach the payer. Teams that use consistent, repeatable workflows for documentation see measurably fewer denials than those relying on individual staff to remember every requirement. 2. Prior Authorization Timing Gaps Prior authorization management is one of the most common sources of reimbursement delays in 2026, and the problems usually come down to timing. The typical scenario: equipment is scheduled, a delivery date shifts, and the authorization window closes before the claim is submitted. By the time the billing team notices, the denial is already issued. What works is treating authorizations as an ongoing operational responsibility rather than a one-time task that gets handed off. Organizations that track expiration dates proactively , through a centralized system with alerts , catch these issues before they turn into denials. Those that manage authorizations reactively keep running into the same problem repeatedly. If your team handles DME billing at volume, authorization tracking alone justifies having a dedicated workflow or support in place. 3. Coding Inaccuracies Coding requirements shift. Modifier rules get updated without much fanfare. And payer-specific interpretation differences mean that what works for one payer may not work for another. Even experienced billing teams miss things when rules change frequently and training doesn’t keep pace. One of the most effective adjustments providers are making right now is treating coding education as continuous rather than annual. Quarterly coding reviews, combined with payer-specific update tracking, reduce claim errors over time in a way that annual refreshers simply don’t. 4. Single-Point Eligibility Verification This is one of the most preventable compliance problems in DME operations, and it still happens constantly. A patient qualifies at intake. Equipment gets scheduled and delivered. Then the payer denies the claim because coverage changed days before delivery. The provider has already absorbed labor, scheduling, and inventory costs , and now has to fight for reimbursement on top of it. Verifying eligibility at multiple points throughout the process, and especially close to the delivery date, significantly reduces this risk. It takes more time upfront but far less time than managing denials and appeals after the fact. 5. Reactive Audit Preparedness Most providers think about audit readiness only after they receive an audit notice. By then, scrambling to organize records and pull documentation is stressful, expensive, and time-consuming. The smarter approach , and the one that consistently protects providers , is treating audit readiness as an ongoing standard rather than an emergency response. That means keeping digital records organized, verifying documentation completeness before claim submission, and running internal compliance reviews on a regular schedule. A practical audit-readiness framework looks like this: How Compliance Problems Hurt Financial Performance This is the part of the conversation that often gets overlooked: compliance issues aren’t just administrative headaches. They’re financial ones. Every denied claim generates additional labor , someone has to research it, prepare an appeal, resubmit, and follow up. Delayed reimbursements affect cash flow predictability. Audit exposure creates financial instability that’s hard to plan around. And when workflows are inconsistent, revenue forecasting becomes nearly impossible. That’s why more DME providers in 2026 are integrating compliance management directly into financial planning. Not treating it as a separate department concern, but recognizing that operational finance and compliance performance are directly connected. Providers who manage compliance proactively tend to have more predictable revenue. Providers who manage it reactively spend a disproportionate amount of time and money cleaning up problems that didn’t need to happen. Technology Helps , But It Isn’t the Whole Answer Automation tools, digital workflow systems, and centralized dashboards are becoming more common across DME operations. And they genuinely help , especially for tracking, reporting, and flagging inconsistencies before they reach the payer. But technology doesn’t replace operational discipline. Compliance errors often happen precisely because teams assume systems
How Compliance Services Keep Healthcare Teams Up To Date

Compliance services keep healthcare teams informed about regulatory updates, billing procedures, and patient data requirements efficiently. Healthcare providers face constant changes in coding rules and Medicare regulations that can affect reimbursements. Effective compliance ensures accurate DME Compliance services and minimizes financial risks for medical practices. Staying current prevents claim denials and supports smooth daily operations. Partnering with expert teams allows staff to focus on patient care rather than administrative tasks. Modern Healthcare Compliance services integrate technology and expertise to streamline processes and reduce errors. Understanding Compliance Services Importance Compliance services keep healthcare teams aligned with the latest industry standards and government regulations efficiently. These services ensure providers follow Medicare and insurance rules properly. Regular updates reduce the risk of billing errors and legal penalties. Staff training improves knowledge of documentation, coding, and submission protocols. Accurate compliance helps practices maintain smooth workflows and enhances financial performance. Outsourcing DME Compliance services ensures specialists handle complex requirements professionally. Key Components of Compliance Services Compliance includes verification, monitoring, and education to prevent billing issues. Compliance services keep healthcare teams updated on claim procedures and denials. Policy reviews, risk assessment, and auditing are essential. Compliance software helps track changes in rules and requirements. Reporting dashboards provide real-time insights into operational performance. Proactive compliance improves reimbursement speed and reduces administrative burdens. Benefits of Professional Compliance Services Partnering with experts strengthens accuracy and efficiency. Healthcare Compliance services improve revenue and minimize risks. Policy Updates Documentation Accuracy Coding Compliance Audit Preparedness Denial Management How DME Compliance Services Work DME Compliance services begin with reviewing documentation and billing workflows for adherence. Documentation & Coding Review Medical records and prescriptions are audited to meet Medicare and insurance standards. Accurate coding ensures claims are submitted correctly without risking denial. Staff training emphasizes continuous education for correct documentation and claim management. Submission Monitoring & Follow-up Submitted claims are tracked, and discrepancies are resolved promptly for timely reimbursement. Proactive interventions reduce stress and administrative delays. Staff receive guidance to correct future errors and maintain ongoing compliance. Common Compliance Challenges Healthcare teams face frequent rule changes and complex claim processes. Denials or delays occur if documentation or coding is incorrect. Staff often lack time for continuous policy education. Inconsistent compliance increases financial risk and potential audits. Manual tracking of updates is time-consuming and error-prone. Utilizing Compliance Services to keep Healthcare Teams informed minimizes these challenges effectively. Additionally, adopting automated tools supports consistent adherence and reduces human errors. Compliance Service Workflow Table DME Compliance services involve a systematic approach for accuracy and efficiency. Stage Action Responsible Party Outcome Policy Update Track the latest regulations Compliance Team Staff awareness Documentation Verify medical records Billing Staff Accurate claims Coding Apply the correct codes Specialists Minimized denials Submission Send claims to payers Billing Team Timely reimbursement Review Monitor compliance metrics Managers Risk mitigation How Compliance Improves Healthcare Operations Compliance services help healthcare teams reduce billing errors and enhance revenue consistency. Practices focus on patient care rather than complex administrative tasks. Outsourcing ensures updates are implemented correctly and promptly. Proper documentation reduces audit risks and legal exposure. Automated tools provide dashboards for decision-making and workflow optimization. By leveraging expert billing solutions, medical practices can streamline operations, enhance financial stability, and deliver higher-quality patient services. Tools and Technologies in Compliance Modern compliance leverages software and integrated solutions for efficiency. Compliance Software Platforms Platforms track regulatory changes, monitor claims, and maintain organized documentation efficiently. Integration with medical records ensures seamless accuracy across billing processes. These systems also provide alerts to staff when updates occur or errors are detected. Analytics & Reporting Real-time analytics highlight errors, track denials, and measure operational compliance. Dashboards allow managers to identify trends and adjust strategies quickly. Automation reduces manual work while maintaining consistent adherence across departments. Why Outsourcing Compliance Services Works External experts provide strategic advantages beyond internal handling. Compliance services keep healthcare teams informed without overburdening staff. Expert Oversight Risk Reduction Time Efficiency Revenue Optimization Scalability Partnering with Easy Billing Services Easy Billing Services LLC offers professional DME Compliance services for accurate billing and documentation. Their team manages claims and regulatory updates from start to finish efficiently. Outsourcing ensures smooth reimbursements while maintaining strict compliance. Transparent reporting keeps providers informed of operational and financial performance. Leveraging their expertise reduces errors and enhances practice profitability. Providers can focus entirely on patient care while staying fully compliant. The firm simplifies DME Compliance services using innovative and professional solutions. Their experts audit, code, and track all claims accurately. Staff receive real-time guidance on updates and denials. Automated systems streamline workflow, reduce errors, and improve reimbursements. Outsourcing to them ensures compliance, efficiency, and peace of mind for healthcare teams. Closing Notes Compliance services keep healthcare teams informed, efficient, and prepared for regulatory changes effectively. Proper compliance safeguards revenue and prevents costly claim errors. Outsourcing ensures expertise, reduces administrative burden, and maintains updated practices. Automated tools and reporting optimize workflow and support decision-making. Healthcare Compliance services and DME Compliance services offer scalable, reliable solutions. Partnering with trusted experts like Easy Billing Services LLC ensures seamless operations and enhanced profitability. Boost your medical practice efficiency today—partner with Easy Billing Services LLC for professional DME Compliance services. For more details, kindly send your queries to info@easybillingservices.com OR call directly at +1 (877) 306-2906. FAQs